A pancreatic cyst does not become dangerous because of its size alone, but because of specific warning signs doctors have learned to watch for inside and around it.
Quick Take
- Two cyst types, mucinous cystic neoplasms and intraductal papillary mucinous neoplasms, carry the real potential to turn cancerous.
- Doctors look for high-risk signs like jaundice, bulging growths inside the cyst, and a widened main pancreatic duct.
- Smaller warning signs, called worrisome features, push doctors toward closer monitoring rather than immediate surgery.
- Guidelines from different medical groups do not all use the exact same cutoff numbers, which matters for patients comparing advice.
- Most pancreatic cysts are found by accident on scans and never turn into cancer.
Why Some Cysts Raise Red Flags and Others Do Not
Not every fluid-filled pocket in the pancreas behaves the same way. Pseudocysts and serous cystadenomas rarely turn dangerous. But mucinous cystic neoplasms and intraductal papillary mucinous neoplasms, known as IPMN, are different. These produce mucin, a slippery substance tied to a real risk of malignant change over time. That distinction, mucin-producing versus not, is the starting point doctors use to sort low-risk cysts from ones that need closer attention.
Finding mucin in a cyst does not mean cancer is coming. It means the cyst belongs to a category capable of changing over years. Think of it like a smoker’s lung versus a nonsmoker’s lung. One carries a higher baseline risk, but that risk still depends on other factors before anyone reaches for a scalpel.
The Signs That Push Doctors Toward Surgery
International guidance updated in 2024 lays out clear high-risk stigmata for IPMN. These include obstructive jaundice caused by a cyst in the head of the pancreas, a bulging growth inside the cyst measuring 5 millimeters or more, a main pancreatic duct dilated to 10 millimeters or beyond, and suspicious or outright positive results from cyst fluid testing. When these show up, the conversation often shifts from watching to operating, especially for main-duct IPMN, which guideline reviews treat as a particularly serious situation warranting a surgical referral.
These are not arbitrary numbers. Each one reflects a pattern doctors have observed across thousands of patients where the odds of hidden cancer climb sharply. Jaundice, in particular, signals that a growth may already be blocking bile flow, a sign the problem has moved beyond a simple fluid pocket.
Worrisome Features Sit in a Gray Zone
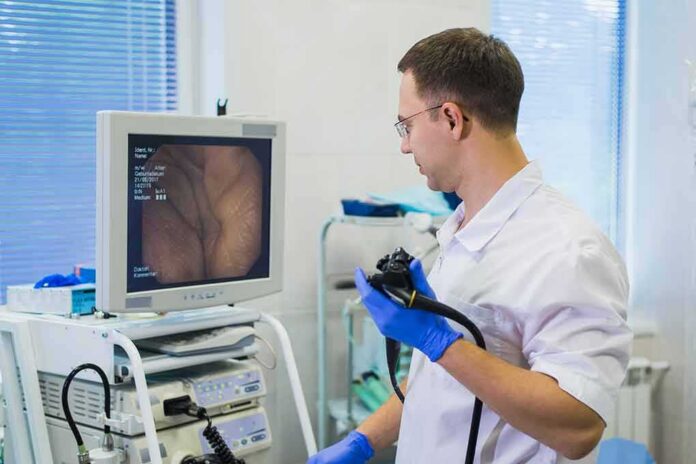
Below the high-risk tier sits a second group called worrisome features. These include a cyst of at least 3 centimeters, smaller bulging growths inside it, thickened or enhancing walls, a duct dilated between 5 and 9 millimeters, elevated levels of a blood marker called CA 19-9, swollen nearby lymph nodes, or a cyst that grows unusually fast. None of these alone proves cancer. They simply earn a cyst closer scrutiny, often through an ultrasound probe passed down the throat called endoscopic ultrasound, plus review by a team of specialists.
Different medical organizations, including the American Gastroenterological Association, the American College of Gastroenterology, and European and Asian panels, do not apply identical numbers to these features. One group’s threshold for ordering an ultrasound biopsy may differ from another’s. That inconsistency is not a sign the science is broken. It reflects genuine, ongoing debate over where caution should tip into action.
Why Doctors Resist Jumping Straight to Surgery
Pancreatic surgery is serious. It carries real risks of complications and a long recovery, which is why doctors do not remove every cyst that shows a single worrisome sign. A large study of patients with low-risk cystic lesions found that only 0.6 percent went on to develop pancreatic cancer, though that rate still ran higher than the general population’s baseline risk. Larger cysts and wider ducts tracked with greater danger, reinforcing why size and duct measurements matter even in lower-risk cases.
Separate population research found cysts are remarkably common. Nearly half of one studied group had a cyst, and over half of those saw some growth in size or number within five years, yet no pancreatic cancer occurred in that same window. Growth alone, in other words, does not equal malignant transformation. It is the combination of growth with high-risk or worrisome features that changes the calculation.
Even imaging has limits. Guideline authors acknowledge that telling a bulging mural nodule apart from a solid mass on a scan can be genuinely difficult before surgery confirms it. That is a technical challenge for radiologists, not evidence that the whole risk-assessment system is unreliable. It simply explains why multidisciplinary review, not a single scan, drives serious decisions.
What This Means for Patients Hearing the Word Cyst
A pancreatic cyst diagnosis is not a cancer diagnosis. It is the start of a structured evaluation built on decades of pooled patient data. Doctors weigh cyst type, size, duct width, internal growths, blood markers, and fluid testing together, not in isolation. Patients who understand that framework can ask sharper questions and avoid both needless panic and needless delay when a scan turns up something unexpected.
The bottom line for anyone handed this diagnosis: ask which specific features your doctor found, which guideline they are following, and whether surveillance or surgery matches your personal risk profile. The numbers behind these decisions are hard-won from real patient outcomes, and that is exactly the kind of evidence-based caution worth trusting over guesswork.
Sources:
youtube.com, ahpba.org, di.aerzteblatt.de, pmc.ncbi.nlm.nih.gov, mdpi-res.com, ncbi.nlm.nih.gov, link.springer.com